Showing posts with label fluoride. Show all posts

Friday, January 27, 2017

Sealants and Fluoride: Benefit to Adult Patients

Dental decay can develop at any time, regardless of a person’s age. A change in diet, change in lifestyle, change in oral self-care habits, the use of prescription medications, or a change in systemic health due to the normal aging process can all affect the caries (decay) susceptibility. Few people remain completely free of decay. Proper oral self-care on your part and properly spaced dental hygiene prevention appointments will go a long way to reduce the opportunity to have new decay begin.
As you age, it is possible that some of your gum tissue will recede, exposing the root surfaces of your teeth. This gum recession can occur from improper brushing (brushing too hard with a hard toothbrush) or as a result of past periodontal problems. The more a tooth and root are exposed, the greater is the surface area you will have to keep clean. Sometimes the teeth with exposed roots are very hard to keep clean. These roots may be sensitive to temperature changes and are often times uncomfortable to brush. Decreased salivary flow helps to create a breeding ground for bacteria to accumulate on the enamel and especially on the root surface. And root decay usually progresses quite quickly!

Goal of Prevention
Your goal should be to keep the dentist from drilling your teeth. Any reasonable preventative measure that is available should be seriously considered. When the dentist drills, you lose. When the dentist does not drill, you win,

Dental Sealants
Although sealants are primarily designed for children, adults who have a history of active decay should consider having sealants placed on the posterior (back) teeth where indicated. We will tell you where it is possible to place the sealants. Even if you have not had a cavity for a long time, consider the application of a sealant as an inexpensive insurance policy for your teeth. Perhaps you would never get decay on the unsealed surfaces. But, just as you insure your home against destruction by fire, a sealant insures the tooth surface from decay. Preventative measures may allow you to avoid having your teeth drilled. You win!  

Topical Fluoride
For a similar reason, we advise the use of topical fluoride treatments for adults. The effectiveness of systemic and topical fluoride in preventing decay is well documented. When a cavity first starts, an application of fluoride might (depending on when it is used) reduce or eliminate the need for drilling.
An alternative to the fluoride treatment we can provide in our office is a daily rinse. If you can rinse with an over-the-counter mouthrinse containing fluoride every night as directed on the rinse label, you do not need the office topical fluoride treatment. If you cannot rinse daily as instructed, you will need the benefit from a stronger office-applied topical fluoride treatment. Your oral health will benefit most from small increments of fluoride that are applied daily rather than one large concentration every 6 months. However, only you know whether you will be faithful to your rinsing routine. When in doubt, let us do it here.

If you have been a patient of Omni Dental Group, you know that we stress prevention of dental disease above all else. Sealants and topical fluoride treatments are two of the more preventative dental measures that we believe will significantly enhance your oral health. 

Monday, August 4, 2014

Dentin Decay

Detect decay by inspecting the color and hardness
Usually, dental decay is fairly easy to detect. When a cavity is just beginning, it is typically identified by a brown or white color or a change in the translucency of the enamel of the tooth. The dentist or dental hygienist uses a special dental instrument called an explorer to feel the suspect area and check its hardness. If the area is hard, in other words, if no break in the enamel layer is detected, we feel there is not a cavity present. If, however, the surface feels soft and the explorer "sticks" in the suspect site, we feel a cavity is present.

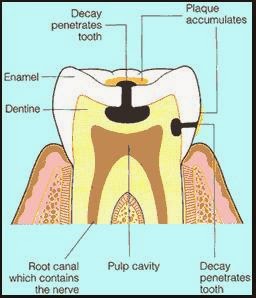
Fluoride makes our enamel stronger, but dentin decay is harder to detect Because of the widespread use and availability of fluoride in our drinking water, foods, and oral care products, we are seeing a different decay pattern. The appearance is different from the typical pattern of decay and more difficult to detect. As the outer surface of the enamel absorbs fluoride (from toothpaste, for example), the enamel becomes very resistant to demineralization and eventual decay. If there is a small break in the integrity of the enamel, a pit or groove where decay-causing bacteria can live, the bacteria can dissolve the enamel in such a way that the hole in the enamel cannot be detected. Once the decay-causing bacteria reach the underlying dentin, the acids eat away at that substance and quickly make a large cavity - but one that still cannot be easily seen or detected. In this way the enamel becomes undermined. A dentist looking at such a small cavity would think it very easy to restore. However, once the decayed portion of the enamel is removed and the dentin becomes visible, the true extent of the damage becomes obvious. The small cavity becomes a big cavity.

One of the major problems with decay that appears to occur only in the dentin is in the detection. If a radiograph is taken a part of the periodic examination process, we may be able to see dentin decay if it is moderate to extensive. Decay seen on radiographs is typically two to seven times greater in the tooth. Modern high-speed radiographic film and reduced x-ray exposure makes it more difficult to detect early decay on radiographs.

You can prevent decay by using fluoride
The conscientious application of a source of topical fluoride, through either an over-the-counter dentifrice or a prescription fluoride product, and thorough plaque removal are essential. Bonded sealants are also an effective protection against dentin decay. We strongly advice these procedures. Periodic examinations at intervals recommended by the dentist catch decay at the earliest possible time. This is the only way to keep small problems from developing into larger problems.

Click here to check out our blog post on foods that cause decay. 
Click here for our post on how to prevent decay.

If you have any questions about dentin decay, please feel free to ask us. 

Wednesday, July 30, 2014

Sealants and Fluoride: Benefit to Adult Patients

Dental decay can develop at any time, regardless of a person's age. A change in diet, change in lifestyle, change in oral self-care habits, the use of prescription medications, or a change in systemic health due to the normal aging process can all affect the caries (decay) susceptibility. Few people remain completely free of decay. Proper oral self-care on your part and properly spaced dental hygiene prevention appointments will go a long way to reduce the opportunity to have new decay to begin.

As you age, it is possible that some of your gum tissue will recede, exposing the root surfaces of your teeth. This gum recession can occur from improper brushing (brushing too hard with a hard toothbrush) or as a result of past periodontal problems. The more a tooth and root are exposed, the greater is the surface area you will have to keep clean. Sometimes the teeth with exposed roots are very hard to keep clean. These roots may be sensitive to temperature changes and are often times uncomfortable to brush. Decreased salivary flow (dry mouth) helps to create a breeding ground for bacteria to accumulate on the enamel and especially on the root surface. And root decay usually progresses quite quickly!

Goal of Prevention
Your goal should be to keep the dentist from drilling your teeth. Any reasonable preventive measure that is available should be seriously considered. When the dentist drills, you lose. When the dentist does not drill, you win.
                               
                                                         Dental Sealants
Please see our blog post on sealants. Although sealants are primarily designed for children, adults who have a history of active decay should consider having sealants placed on the posterior (back) teeth where indicated. We will tell you where it is possible to place the sealants. Even if you have not had a cavity for a long time, consider the application of a sealant as an inexpensive insurance policy for your teeth. Perhaps you would never get decay on the unsealed surfaces. But, just as you insure your home against destruction by fire, a sealant insures the tooth surface from decay. Preventive measures may allow you to avoid having your teeth drilled. You win! 

Topical Fluoride
For a similar reason, we advise the use of topical fluoride treatments for adults. The effectiveness of systemic and topical fluoride in preventing decay is well documented. When a cavity first starts, an application of fluoride might (depending on when it is used) reduce or eliminate the need for drilling.
Fluoride Varnish

An alternative to the fluoride treatment we can provide in our office is a daily rinse. If you can rinse with an over-the-counter mouth rinse containing fluoride every night as directed on the rinse label, you do not need the office topical fluoride treatment. If you cannot rinse daily as instructed, you will need the benefit from the strong office-applied topical fluoride treatment. Your oral health will benefit most from small increments of fluoride that are applied daily rather than one larger concentration every 6 months. However, only you know whether you will be faithful in your rinsing routine. When in doubt, let us do it here.

We stress prevention of dental disease above all else. Sealants and topical fluoride treatments are two of the more important preventive dental measures that we believe will significantly enhance your oral health.

Tuesday, July 29, 2014

Seal the Deal: Everything You Need To Know About Sealants

What are dental sealants?  

Dental sealants represent one of the greatest advances in modern dentistry. Unfortunately, too many children do not receive the protective benefits of dental sealants. Dental sealants are clear protective coatings that are easily applied; they cover the tooth surface, preventing bacteria and food particles from settling into the pits and fissures (grooves) of the teeth. It is a thin coat of plastic that is painted on the surface of teeth, usually the premolars and molars in order to prevent caries.

Decay on back teeth, premolars, and molars usually begins in the grooves and fissures that normally exist on the biting surfaces of the back teeth.  Dental sealants, available since the 1960s, are clear plastic coatings that can be placed on the biting and grinding surfaces of posterior teeth.  These sealants prevent the formation of decay on the treated surfaces.  Sealants can even be placed of teeth with small areas of decay known as incipient carious lesions.  The sealants will stop the customary progress of tooth destruction.  

Effectiveness
It can remain on the tooth from 3 to more than 20 years, depending on the tooth, type of sealant used, and the eating habits of the patient.  It can only be placed on teeth that have not been previously restored.
It is well known that the use of fluoride increases the resistance of enamel to decay. Unfortunately, the pits and fissures of the teeth do not benefit from the effects of fluoride as greatly as smooth enamel surfaces do. Scientific studies have proved that properly placed dental sealants are 100% effective in protecting development of cavities in sealed tooth surfaces. 

Why sealants are necessary
The narrow width and uneven depth of pits and fissures make them ideal places for the accumulation of food and acid-producing bacteria. Saliva, which helps to remove food particles from other areas of the mouth, cannot clean deep pits and fissures. Pits and fissures on the teeth are so tiny that even a single toothbrush bristle is too large to enter for cleaning purposes. Another difficulty associated with deep pits and fissures is that the enamel that lies at the base of the fissures is thinner than the enamel around the rest of the tooth. This means that not only can deep narrow fissures make it more likely that tooth decay will occur, but any decay that does form will penetrate through the thin enamel and progress more quickly into the pulp.

We, at this office, are dedicated to the prevention of oral disease.  It is clear that if the initial decay is prevented from beginning or is small enough to use a sealant, there is a great savings in time, money, discomfort, and tooth structure.  Decayed teeth must have the decay removed by drilling, then they must be filled.  This drill and fill may have to be done several times over the patient's lifetime as the filling ages and needs replacement.  We strongly suggest that patients who have teeth that can be successfully protected with a sealant material consider having this procedure performed as soon as possible.


How sealants work
The sealant acts as a physical barrier that prevents decay. Small food particles and plaque (bacteria) cannot penetrate through or around a sealant. As long as the sealant remains intact, the tooth is protected. However, if part of the sealant or bond is broken, the sealant protection is lost. 

A study completed in 1991 found that one application of sealant reduced biting surface decay 52% over a 15-year period.  Another study, completed in 1990, showed that decay on biting surfaces could be reduced 95% over 10 years if 2% to 4% of the sealants were routinely repaired each year.  We expect sealants to last many years. After a sealant is applied it can last up to ten years, however regular check-ups are recommended since they can chip or wear off. Replacing or repairing sealants, as needed, on an ongoing basis will give the best protection. 

A sealant is not meant as a substitute for proper brushing and flossing habits. The effectiveness of the sealant is reduced if oral self-care is neglected. Also, cavities can still form on untreated surfaces. Therefore, a topical fluoride treatment remains an essential and necessary preventative aid.

Application of sealants
The sealant is placed on the tooth through a chemical/mechanical bonding procedure.  There is not drilling or local anesthesia required for the sealant application procedure.  It is entirely painless.

Problems with sealants
On occasion, teeth with very small initial carious lesions may be inadvertently sealed, or some bacteria may remain beneath the sealant. It was one believed that if this were to occur, decay would develop under the sealant. However, numerous studies have shown that this does not occur. Bacteria cannot survive beneath a properly placed sealant because the carbohydrates that they need to survive cannot reach them. Studies have shown that the number of bacteria in small, existing carious lesions that had been sealed actually decreased dramatically over time. The most important factor is that the sealant must be properly placed.

When sealants are used
Sealants are used primarily on children, but in certain circumstances, adults also can benefit from their use. Children and teenagers are the best candidates for sealants. Children are prone to caries from age 6-14 and applying a sealant as soon as a child’s permanent molars and premolars erupt can be a great way to protect your child from tooth decay. Some maxillary central and lateral incisors may have deep pits that could be protected by sealants. Sealants are indicated for teeth with deep pits and fissures, preferably in recently erupted teeth (i.e., within previous 4 years). Sealants should be used as part of a prevention program that includes the use of fluorides, dietary considerations, plaque control, and regular dental examinations.

We especially advise that children have the sealant applied to their teeth as soon as the teeth break through the gum and the biting surfaces of the teeth are no longer covered with gum tissue.  If the teeth cannot be totally isolated from the moisture in the mouth during the bonding process, it is likely that the sealant will not remain on the tooth for as long a period of time as expected.  The sealant is most often applied to permanent teeth, but sometimes a situation arises in which it would be beneficial to have the sealant applied to a primary tooth.

In both 1984 and 1994, sealants have been recommended by the U.S. Public Health Services and Surgeon General of the United States, among others. We know that sealants are one of the most important treatments available for prevention of dental decay.

If you have any questions about sealants, please feel free to ask us.

Thursday, July 24, 2014

Sensitive Teeth

Teeth can become sensitive for many reasons. Sometimes, the sensitivity is an indication of a potentially serious problem. Other times, the dentally related problem may be small but the effects (the sensitivity) are extremely aggravating. 

What do we mean when we say "sensitive teeth?"
Twinges of pain or discomfort in our teeth in certain situations such as drinking or eating cold things, drinking or eating hot things, eating sweets, and touching the teeth with other teeth or the tongue. Your symptoms will involve reactions to temperature or pressure. Sensitivity to cold drinks or foods is the most common symptom. 

Two types of sensitivity:

1. Dentinal sensitivity
When the dentin (middle layer) of a tooth is exposed. Normally, dentin is covered by enamel. Dentin becomes exposed when the outer protective layers of enamel wear away. Dentin contains tiny openings called tubules. Inside each tubule lies a nerve branch that comes from the tooth's pulp (the nerve center of the tooth). When the dentin is exposed, cold or hot temperature or pressure can affect these nerve branches, causing sensitivity.

Causes:
  • Inadvertent notching of the tooth surface and/or recession of the gum tissue (exposing the root surface of the tooth) caused by improper brushing: either brushing too hard, brushing with a toothbrush that is too hard, or using an improper brushing technique, which will wear away the enamel layer. This sensitivity can range from mild to extreme; the degree of sensitivity does not appear to be related to the size of the root exposure or notch.
  • Poor oral hygiene, allowing tartar to build up at the gum line
  • Untreated cavities
  • An old filling with a crack or leak
  • Receding gums that expose the tooth's roots, often caused by periodontal disease
  • Gum surgery that exposes the tooth's roots
  • Tooth whitening in people who have tooth roots that already are exposed
  • Frequently eating acidic foods or drinking acidic liquids 
  • Purposeful repositioning of the gum tissue during gum surgery can also lead to tooth sensitivity. While recession from brushing is slow, gum recession following gum repositioning occurs very quickly. The portion of the tooth once covered with gum and bone may now be exposed.  Root sensitivity in these instances can be quite severe and immediate. It can sometimes last four months or years if not treated.
2. Pulpal sensitivity
The reaction of the tooth's pulp. The pulp is a mass of blood vessels and nerves in the center of each tooth. Pulpal sensitivity affects only a single tooth.
Causes:
  • Decay or infection. When a tooth is decayed, temperature changes and sweets will make it sensitive. The solution can be as simple as removing the decay and placing an appropriate restoration.
  • A recent filling. A tooth may be sensitive to cold for several weeks after you get a filling. The metals in amalgam (silver) conduct the cold very well, transmitting it to the pulp. Bonded (tooth-colored) fillings require etching the tooth with acid before the filling is placed. In some cases, this etching removes enough enamel to make the tooth sensitive. If a filling is defective or failing, leakage around the filling may cause the tooth to become sensitive. The solution can be as simple as removing the defective filling and placing an appropriate restoration.
  • Excessive pressure from clenching or grinding
  • A cracked or broken tooth. If the tooth is fractured, you may be sensitive to temperature changes or when chewing food. This fracture condition may be hard to diagnose. If you think you might have this type of sensitivity, read our blog post on "cracked tooth syndrome."
  • A tooth can become sensitive after it has been prepared (drilled) for a restoration (filling). You may have been anesthetized during the procedure, so you did not feel any discomfort when the nerve in the tooth reacted to the heat generated by the drill. The closer the drill comes to the nerve, the more likely it is to cause a sensitivity problem. The high-speed rotation of the bur in the drill generates heat, and the response of the nerve to heat is inflammation. This inflammation is felt by you as a "sensitivity."  If the decay, fracture, or drilling was not too deep, this sensitivity will decrease over time. A week to a month or two is not an unusual length of time for the sensitivity to disappear. A good sign is the continued decrease of sensitivity.  However, if the occlusion (bite) is off after the restoration has been placed, the tooth may either become sensitive or may stay sensitive. Once the bite is adjusted, though, the sensitivity should disappear.
  • A dying nerve. This can be the result of a deep cavity. Commonly, the sensitive tooth holds an old large filling. The nerve may be damaged during drilling and the nerve has been dying gradually ever since. If this is the problem, the tooth will need endodontic treatment (root canal treatment).
See this post about the 10 biggest causes of tooth sensitivity.

How will the doctor diagnose sensitivity?
Your dentist will look at your dental history and will examine your mouth. You also will need x-rays to show if there is decay or a problem with the nerve. The dentist will ask about your oral habits. Grinding or clenching your teeth can contribute to sensitivity. Your dentist also will look for decay, deep fillings, and exposed root surfaces. During the consultation, your dentist uses an instrument called a spray gun to dispense air across every area of each tooth in order to locate the sensitivity. He or she may use an explorer - a metal instrument with a sharp point - to test teeth for sensitivity.
 
How will it be treated?
  • Your dentist or dental hygienist will clean your teeth. If your teeth are too sensitive to be cleaned, your dentist may use a local anesthetic or nitrous oxide before the cleaning. 
  • If there is a notch in the tooth or the shape of the defect is appropriate, the defect is restored (filled in) with a bonded material. This can give immediate relief -- sometimes partially, sometimes fully. 
  • When there is no defect to be restored, the exposed and sensitive root surfaces are covered with a dentin-bonding or other material. This material is invisible and has very little thickness, so you do not notice any change in the appearance of the tooth; but it works. It may have to be reapplied after several months because the bonding material has worn away by tooth-brushing.
  • If you have pulpal sensitivity and the tooth's nerve is damaged or dying, you will need a root canal. Your dentist will remove the nerve and place a non-reactive substance in the space where the nerve was. The tooth will no longer have a continuous barrier of enamel to protect it. Therefore, it will be restored with either a composite filling or a crown.
  • Your dentist may apply a fluoride varnish to protect your teeth. This temporarily reduces sensitivity and strengthens your teeth.
  • Using fluoride toothpastes and fluoride mouth rinses are home will help to reduce sensitivity. You can also buy toothpastes just for sensitive teeth. You should choose a fluoride mouth rinse that uses neutral sodium fluoride.
How can I prevent it?
If you have any questions about tooth sensitivity, please feel free to call our office for a consultation at (512) 250 - 5012.

Tuesday, July 15, 2014

Prevention of Decay

What is dental decay, and how do dentists fix it?
Dental caries (decay) is a bacterial infection, first of the enamel, then of the dentin of the tooth. The tradition in dentistry has been to surgically remove the diseased portion of the tooth by "drilling" out the decay and then filling the resulting hole in the tooth with some inert material. As most adults know, this procedure will be performed over and over again when new decay begins or when the filling (often silver) breaks or the tooth fractures.

Click here to learn about decay in young children.

Why should I practice prevention?
Would it not be better to eliminate the cause of the infection and thus not be forced to have big holes drilled in the teeth? We believe the bacterial cause of the infection should be addressed.

How do I prevent dental decay?
There are several positive steps that you can take to reduce your risk of dental decay. 

A. At the dentist's office
1. First, all the active decay in your mouth should be treated immediately. 

2. Next, all teeth that would benefit from sealants should be treated. 
  • Why? This will prevent bacteria from reaching into the pits, fissures, and grooves that normally exist on the occlusal (biting) surfaces of teeth. Any stray bacteria that may still be in the sealed area are effectively cut off from their source of food and become inactive. Although sealants are most effective on teeth that have not been previously restored, they can be successfully placed on teeth filled with bonded fillings.
3. The infection can be treated with antimicrobials. 

4. We believe that the use of a fluoridated mouthrinse twice daily or use of a prescription fluoridated dentifrice as directed provides a great advantage. 
5. We may also prescribe a chlorhexidine mouthrinse, an antimicrobial oral rinse that has a great effect on Streptococcus mutans.

B. In your daily life
6. Your diet and oral self-care are important in dental decay prevention. When you eat junk food and drink sugary liquids, your teeth are more prone to decay. The more frequently you snack, the more prone your teeth will be to decay. 

7. If your brushing and flossing are not effective, your teeth will be more prone to decay. When you can't brush after a meal, at least rinse your mouth with water within 15 minutes to dilute the acids forming from the ingested food or drink. 

8. If you have a diminished salivary flow, take frequent sips of water during the day to help dilute the acids produced by the bacteria.

What if decay keeps coming back?
If you have a continuing problem with active decay, we recommend more frequent preventive recare appointments. It has been repeatedly shown that patients who have good oral self-care and maintain a recare interval of 3 to 4 months have many fewer dentally related (cavities or gum disease) problems.

Present-day dental suggestions are based on proven scientific information. You might need to have your teeth cleaned by the hygienist twice each year, or you may need to be seen more frequently. 

For certain individuals, we also suggest testing the oral bacterial levels to determine the magnitude and presence of a Streptococcus mutans infection and to determine your risk level for future dental disease.

If you have any questions about the prevention of dental decay, please feel free to ask us.